




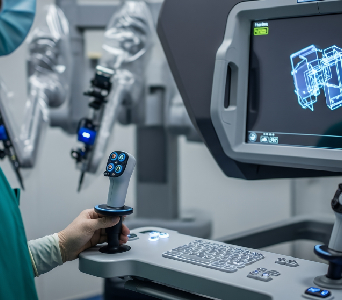
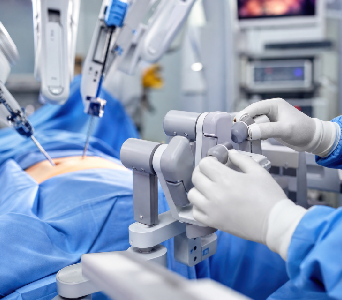
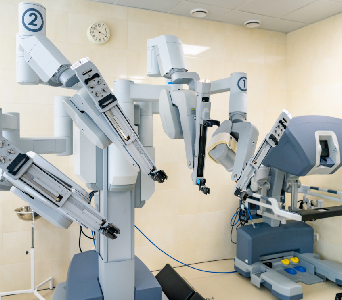
Robotic-assisted cancer surgery is a minimally invasive surgical approach in which a surgeon uses a robotic system to perform selected cancer operations through small incisions. The system typically includes a surgeon’s console, a high-definition three-dimensional camera and instrument-bearing arms positioned beside the patient.
The surgeon controls every movement of the instruments from the console. The robotic system does not operate independently, make decisions or perform any part of the surgery on its own. It translates the surgeon’s hand movements into precise movements of specialised instruments inside the body.
Robotic assistance may be used for selected cancers in areas such as the chest, abdomen, pelvis, urinary system, reproductive organs, gastrointestinal tract and head and neck. Depending on the cancer type and stage, the operation may involve removing the tumour with an appropriate margin, removing part or all of an affected organ, or sampling or removing nearby lymph nodes.
At Apollo Cancer Centres, robotic-assisted surgery is recommended only when it can achieve the required oncological goals safely. Surgical oncologists work with medical oncologists, radiation oncologists, radiologists, pathologists, anesthetists and rehabilitation specialists to select the most appropriate surgical approach for each patient.
- Have a localised solid tumour that can be removed safely through a minimally invasive approach
- Require removal of a tumour, part or all of an affected organ, or selected nearby lymph nodes
- Have a tumour in an area where enhanced visualisation and flexible instruments may assist precise dissection
- Need surgery in a narrow or difficult-to-access anatomical area
- May benefit from preservation of nearby organs, nerves, blood vessels or other important structures where oncologically appropriate
- Need staging surgery to assess whether cancer has spread within a body cavity or to nearby lymph nodes
- Have received chemotherapy, immunotherapy or radiation therapy and remain suitable for surgery
- Have selected recurrent disease that can be removed using a robotic-assisted approach
- Are medically fit for anesthesia, surgical positioning and the other requirements of the planned procedure
How the Procedure is Performed
Before the Procedure
Before robotic-assisted cancer surgery:
The surgical team reviews the biopsy, imaging scans, laboratory results, medical history and current medications.
Additional imaging, endoscopy or other investigations may be recommended to assess the extent of the cancer and plan the operation.
The patient’s fitness for surgery and anesthesia is evaluated. This may include blood tests, heart and lung assessments, and consultation with an anesthetist.
The case may be reviewed by a multidisciplinary tumour board to determine whether surgery should be performed first or combined with treatments such as chemotherapy, immunotherapy or radiation therapy.
The surgeon explains the goal and extent of the operation, expected benefits, possible risks, alternatives and anticipated recovery.
The possibility of removing nearby lymph nodes, part or all of an affected organ, or neighbouring structures is discussed when relevant.
The surgeon explains that the procedure may need to be completed using conventional minimally invasive surgery or through a larger open incision if required for safety.
The possible need for drains, tubes, blood transfusion or a temporary or permanent stoma is discussed whenever it can be anticipated.
Instructions are provided about fasting, medications, bowel preparation where required, smoking cessation and admission to the hospital.

During the Procedure
Robotic-assisted cancer surgery is usually performed under general anesthesia.
The patient is carefully positioned according to the organ being treated, and the surgical team continuously monitors vital functions throughout the operation.
The surgeon makes one or more small incisions for the camera and surgical instruments.
The robotic system is positioned beside the patient, and the camera and instruments are connected to the system’s arms.
The surgeon sits at a console in the operating room and views the surgical area through a magnified, high-definition three-dimensional display.
Every movement of the instruments is directly controlled by the surgeon. The system does not perform the operation independently.
The instruments can move within confined anatomical spaces, allowing the surgeon to dissect tissue and perform the planned operation.
The tumour is removed with an appropriate margin of surrounding tissue whenever feasible. Part or all of an affected organ may also need to be removed.
Nearby lymph nodes may be sampled or removed when required for cancer staging or treatment.
In selected cases, a pathologist may examine tissue during the operation to assess a surgical margin or confirm the nature of a suspicious area.
The removed tissue is placed in a protective retrieval bag when appropriate and taken out through an incision that may be slightly enlarged.
If the operation cannot be completed safely using the robotic-assisted approach, the surgeon may change to conventional minimally invasive or open surgery.
At the end of the procedure, the instruments are removed, the incisions are closed and the patient is transferred to a recovery area for monitoring.
The duration of surgery varies according to the organ involved and the complexity of the procedure. Robotic-assisted surgery is not necessarily shorter than other surgical approaches because additional time may be required for positioning and setting up the system. The surgeon will explain what to expect for the planned operation.

After the Procedure
Recovery: Recovery depends on the type and extent of surgery, the organ involved, the patient’s overall health and whether the procedure was completed robotically or changed to another approach.
Hospital Stay: Some patients may go home within a day, while others may remain in hospital for several days after major cancer surgery. The care team monitors pain, wound healing, breathing, circulation, bowel and bladder function, nutrition and mobility.
Pain Management: Pain is managed using a personalised combination of medicines. Discomfort is usually concentrated around the incisions. After abdominal or pelvic procedures, temporary abdominal bloating or shoulder-tip discomfort may occur because of the gas used to create operating space.
Nutrition and Mobility: Fluids and food are restarted according to the operation and the return of normal body functions. Patients are encouraged to sit up, perform breathing exercises and begin walking as soon as it is safe to reduce the risk of chest infections and blood clots.
Incision and Drain Care: The team provides instructions for caring for the incisions and for any drains, tubes or stoma. Patients are advised which symptoms are expected and which require prompt medical attention.
Resuming Routine: Some patients may return to light activities sooner than after a comparable open operation, but recovery still depends mainly on the extent of the cancer surgery. Heavy lifting, strenuous exercise, driving and return to work should follow the surgeon’s individual advice.
Follow-up Care: Follow-up appointments are scheduled to assess healing, review the histopathology report and discuss the next stage of treatment. Rehabilitation, nutrition, pain management, psychological support or stoma care may be arranged according to the patient’s needs.

Key Advantages
- Fever, chills or increasing weakness
- Worsening pain that is not controlled by prescribed medication
- Increasing redness, warmth, swelling, discharge or bleeding from an incision
- Persistent vomiting, increasing abdominal swelling or inability to eat or drink
- Shortness of breath, chest pain or coughing up blood
- New swelling or pain in a leg
- Difficulty passing urine, reduced urine output or an unexpected change in bowel function
- New weakness, numbness or persistent pain in an arm or leg
- A problem with a drain, tube or stoma
- Any symptom identified by the surgical team as specific to the procedure

Continuum of Care
Robotic-assisted cancer surgery is one part of a coordinated treatment pathway. After surgery, patients may receive:



