




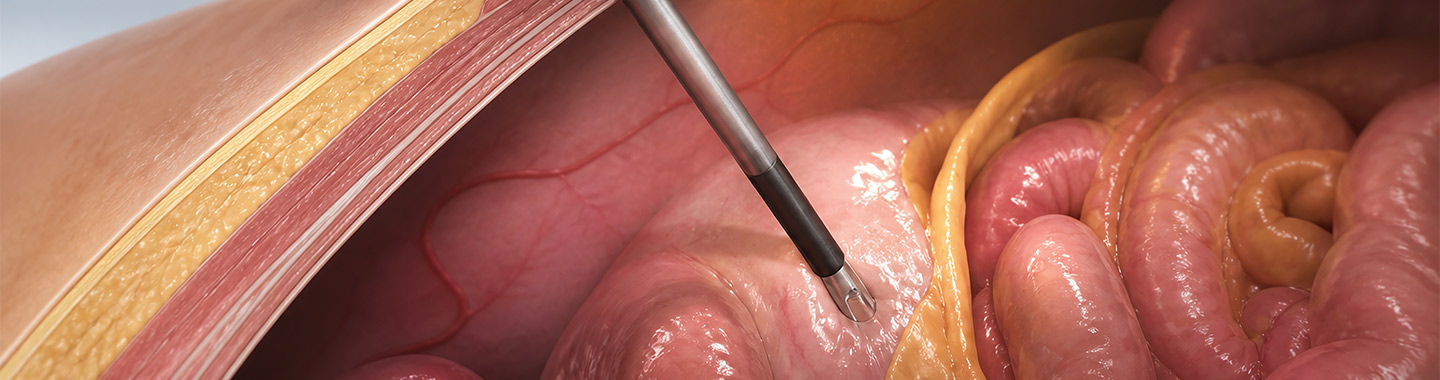
Hyperthermic Intraperitoneal Chemotherapy, or HIPEC, is a specialised treatment used for selected cancers that have spread to the peritoneum, the thin membrane lining the abdominal cavity and covering many abdominal organs.
HIPEC is usually performed immediately after cytoreductive surgery. The surgeon first removes as much visible cancer as safely possible. A heated chemotherapy solution is then circulated directly within the abdominal cavity to treat microscopic cancer cells that may remain on the peritoneal surfaces.
Unlike intravenous chemotherapy, which travels through the bloodstream, HIPEC delivers chemotherapy directly to the area where the cancer is located. This allows the abdominal surfaces to be exposed to a concentrated dose of the medicine. Heating the solution may enhance the effect and tissue penetration of certain chemotherapy drugs.
HIPEC is not a treatment for all cancers or all patients with abdominal metastases. It may be considered for selected peritoneal surface cancers originating from the appendix, colon, rectum, ovary or other abdominal organs, as well as primary peritoneal malignancies such as peritoneal mesothelioma. Its role varies by cancer type, disease extent and the available clinical evidence.
At Apollo Cancer Centres, patients being considered for HIPEC are evaluated by a multidisciplinary team that may include surgical oncologists, medical oncologists, radiologists, pathologists, anesthetists, critical-care specialists, nutritionists and rehabilitation teams. The expected benefit is carefully balanced against the complexity and risks of cytoreductive surgery and HIPEC.
- Have a cancer that has spread predominantly to the peritoneal surfaces
- Have a cancer type for which cytoreductive surgery with HIPEC may offer clinical benefit
- Have disease that appears removable or reducible to a very small amount through cytoreductive surgery
- Have limited disease outside the abdominal cavity, or no disease outside it, depending on the cancer type and treatment goal
- Have selected recurrent cancer confined mainly to the abdomen or pelvis
- Have responded to systemic treatment and remain suitable for major surgery
- Are medically fit to undergo a long and complex operation
- Have adequate heart, lung, kidney, liver and bone-marrow function for the planned treatment
- Have a nutritional and functional status that supports recovery after major surgery
- Understand that systemic chemotherapy or another treatment may still be required before or after HIPEC
How the Procedure is Performed
Before the Procedure
Before HIPEC:
The care team reviews the biopsy, imaging scans, previous cancer treatments, laboratory results, medical history and current medications.
Detailed imaging is used to assess the distribution of cancer within the abdomen and look for disease elsewhere in the body.
In selected cases, diagnostic laparoscopy may be performed to assess the extent of peritoneal disease and whether adequate cytoreduction appears achievable.
The case is reviewed by a multidisciplinary tumour board to determine whether HIPEC is appropriate and when it should be performed in relation to systemic treatment.
The patient’s fitness for major surgery and anesthesia is assessed. This may include blood tests, heart and lung evaluation, kidney and liver function tests, and consultation with an anesthetist.
Nutritional status, weight, strength and daily functioning are evaluated because they can affect recovery.
The surgeon explains the expected extent of cytoreductive surgery and which organs or structures may need to be partially or completely removed.
The possibility of bowel resection, reconstruction, blood transfusion or a temporary or permanent stoma is discussed whenever it can be anticipated.
The medical and surgical teams select the chemotherapy medicine, dose, temperature and circulation time according to the cancer type, treatment protocol and patient’s health.
Nutritional support, exercise, breathing exercises or optimisation of existing medical conditions may be recommended before surgery.
Instructions are provided about fasting, medications, bowel preparation where required, smoking cessation and hospital admission.

During the Procedure
HIPEC is generally performed as part of a two-stage operation - first is the cytoreductive surgery and then HIPEC administration.
The procedure is performed under general anesthesia.
The surgeon opens the abdomen and carefully examines the peritoneal surfaces and abdominal organs to assess the extent of disease.
First, as much visible cancer as safely possible is removed.
Depending on the distribution of cancer, the procedure may involve removing affected areas of the peritoneal lining and parts of involved organs.
Sections of the bowel, reproductive organs, spleen, gallbladder, omentum, diaphragm lining, liver surface or other tissues may need to be removed in selected cases.
Bowel or other hollow organs may be reconnected after the affected section is removed. A temporary or permanent stoma may occasionally be required.
To perform HIPEC, tubes are positioned within the abdominal cavity and connected to a specialised perfusion system.
A chemotherapy solution is heated to a carefully controlled temperature and circulated throughout the abdomen.
The surgical team gently distributes the solution so that it reaches the abdominal and pelvic surfaces.
The patient’s body temperature, circulation, urine output, blood chemistry and other vital functions are closely monitored throughout the treatment.
The chemotherapy solution is circulated for a set period determined by the treatment protocol.
At the end of HIPEC, the solution is drained from the abdomen.
The abdominal cavity is checked, any required surgical connections are completed or assessed, and drains or tubes are placed when necessary.
The incision is closed, and the patient is transferred to a recovery area, high-dependency unit or intensive care unit for monitoring.
Cytoreductive surgery with HIPEC may take several hours. The duration depends mainly on the extent of cancer, the organs involved, the cytoreductive procedures required and the HIPEC protocol being used.

After the Procedure
Critical-Care Monitoring: Some patients require monitoring in a high-dependency or intensive care unit after surgery. The care team monitors breathing, circulation, kidney function, fluid balance and recovery from anesthesia.
Hospital Stay: Hospital stay may range from several days to a few weeks, depending on the extent of surgery, recovery of organ function and whether complications occur.
Pain Management: Pain is managed using a personalised combination of medicines and, when appropriate, an epidural, nerve block or another regional pain-relief technique.
Nutrition: Fluids and food are restarted gradually as bowel function returns. Intravenous nutrition or tube feeding may occasionally be required after extensive surgery.
Kidney and Blood Monitoring: Blood counts, kidney function, liver function and electrolyte levels are monitored because both major surgery and the chemotherapy used during HIPEC can affect them.
Mobility and Breathing Exercises: Patients are encouraged to perform breathing exercises, sit up and begin walking as soon as it is safe. This helps reduce the risk of chest infections, muscle loss and blood clots.
Bowel and Bladder Function: The care team monitors the return of bowel function and urine output. Temporary slowing of the bowel is common after extensive abdominal surgery.
Wound, Drain and Stoma Care: Patients and caregivers receive instructions about caring for the incision and any drains, tubes or stoma.
Histopathology Review: Removed tissues are examined to confirm the cancer type, extent of involvement, lymph-node findings and other features that may guide further treatment.
Further Cancer Treatment: Systemic chemotherapy, targeted therapy, immunotherapy or another treatment may still be recommended after recovery.
Resuming Routine: Recovery commonly takes several weeks or months because HIPEC is usually combined with major abdominal surgery. Return to work, driving, exercise and normal activities should follow individual medical advice.
Follow-up Care: Follow-up appointments assess healing, nutritional recovery, organ function and the next stage of cancer treatment.

Key Advantages



- Fever, chills or increasing weakness
- Worsening pain that is not controlled by prescribed medication
- Increasing redness, warmth, swelling, discharge or bleeding from the incision
- Persistent vomiting, increasing abdominal swelling or inability to eat or drink
- Failure to pass urine, gas or stool as advised by the surgical team
- New or worsening diarrhoea, constipation or another unexpected change in bowel function
- Shortness of breath, chest pain or coughing up blood
- New swelling or pain in a leg
- Reduced urine output or a marked change in urine
- Unusual bruising, bleeding or persistent mouth ulcers
- A problem with a drain, feeding tube, urinary tube or stoma
- Sudden weakness, dizziness, confusion or fainting
- Any symptom identified by the surgical team as specific to the procedure or chemotherapy used
Continuum of Care
HIPEC is one component of a coordinated treatment pathway for selected peritoneal surface cancers. After treatment, patients may receive:



