




Pressurised Intraperitoneal Aerosol Chemotherapy, or PIPAC, is a minimally invasive method of delivering chemotherapy directly into the abdominal cavity. It is used in selected patients with cancer that has spread to the peritoneum, the thin membrane lining the abdominal cavity and covering many abdominal organs.
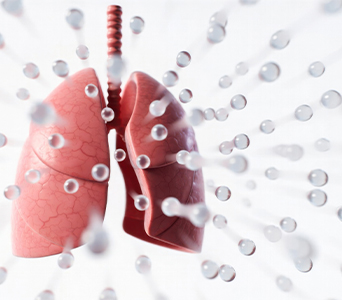
During PIPAC, chemotherapy is converted into a fine aerosol and introduced into the abdomen under controlled pressure through a specialised device. The aerosol is intended to distribute the medicine across the peritoneal surfaces and help it penetrate superficial tumour deposits.
PIPAC is performed through laparoscopy using small incisions. It does not usually involve extensive tumour removal during the same procedure. Because it is less extensive than cytoreductive surgery with HIPEC, PIPAC may be considered for selected patients whose peritoneal disease cannot be completely removed or who are not suitable for major cytoreductive surgery.
The treatment may be repeated at planned intervals, allowing the team to inspect the peritoneal cavity, take biopsies and assess how the disease is responding. PIPAC may be used alone or alongside systemic chemotherapy as part of a carefully coordinated treatment plan.
PIPAC remains an evolving treatment, and its place in care differs by cancer type and healthcare setting. It is not established as standard treatment for all cancers involving the peritoneum. It should be offered by an experienced multidisciplinary team, often within a structured treatment protocol or clinical trial.
At Apollo Cancer Centres, patients being considered for PIPAC are evaluated by surgical oncologists, medical oncologists, radiologists, pathologists, anesthetists and other specialists. The team considers the available evidence, previous treatment, expected benefit, possible risks and other treatment options before recommending the procedure.
- Have cancer that has spread predominantly to the peritoneal surfaces
- Have peritoneal disease that cannot be completely removed through cytoreductive surgery
- Are not suitable for major cytoreductive surgery with HIPEC because of the extent or distribution of disease
- Have persistent or progressive peritoneal disease despite systemic treatment
- Have a cancer type for which PIPAC is being evaluated or used within a specialist treatment protocol
- May benefit from repeated local treatment of the peritoneal cavity
- Need biopsies or direct assessment of peritoneal disease during treatment
- Have symptoms such as recurrent fluid accumulation in the abdomen that may improve with local disease control
- Have adequate heart, lung, kidney, liver and bone-marrow function for the planned procedure and chemotherapy
- Are medically fit to undergo general anesthesia and laparoscopy
- Do not have a bowel obstruction or another condition that would make laparoscopic access unsafe
- Understand that PIPAC may not replace systemic chemotherapy or other cancer treatments
How the Procedure is Performed
Before the Procedure
Before PIPAC:
The care team reviews the biopsy, imaging scans, previous cancer treatments, laboratory results, medical history and current medications.
Imaging is used to assess the distribution of disease within the abdomen and look for cancer elsewhere in the body.
The case is reviewed by a multidisciplinary tumour board to determine whether PIPAC is appropriate and how it should be coordinated with systemic treatment.
The patient’s fitness for general anesthesia and laparoscopy is assessed.
Blood tests are performed to check blood-cell counts, kidney function, liver function and electrolyte levels.
The team assesses for bowel obstruction, infection, extensive abdominal adhesions or another condition that may make the procedure unsafe.
The chemotherapy medicine and dose are selected according to the cancer type, previous treatments, organ function and treatment protocol.
The surgeon explains that laparoscopic access may not be possible if extensive scar tissue or disease is found. In this situation, PIPAC may need to be abandoned.
The planned number and timing of treatment cycles are discussed. Further procedures depend on recovery, treatment response and whether the disease progresses.
The expected benefits, limitations, investigational status, possible risks and alternative treatments are explained.
Pregnancy must be excluded where relevant because chemotherapy can harm an unborn baby. Contraception advice may be provided to patients and partners according to the medicines used.
Instructions are provided about fasting, medications and hospital admission.

During the Procedure
PIPAC is performed in an operating room under general anesthesia.
The surgeon makes one or more small incisions in the abdomen.
Gas is introduced to create a working space, and a laparoscope with a camera is inserted.
The surgeon examines the abdominal cavity and assesses the distribution of peritoneal disease.
Any accumulated abdominal fluid, known as ascites, may be drained and sent for laboratory examination.
Small tissue samples may be taken from selected tumour deposits for histopathology and assessment of treatment response.
The extent of peritoneal disease is documented using an appropriate scoring or assessment method.
If safe access is possible, a specialised nebulising device is introduced into the abdomen.
The chemotherapy solution is delivered through the device as a fine pressurised aerosol.
The abdomen remains closed and sealed while the aerosol is distributed for a set period.
The operating room follows strict safety measures to protect healthcare personnel from chemotherapy exposure.
At the end of the treatment period, the aerosol is removed through a closed waste-management system.
The instruments are withdrawn, the gas is released and the small incisions are closed.
The patient is transferred to a recovery area for monitoring.
The procedure itself is usually shorter and less extensive than cytoreductive surgery with HIPEC. The total time in the operating room includes anesthesia, laparoscopic assessment, biopsies, chemotherapy administration and safe removal of the aerosol.

After the Procedure
Recovery Monitoring: The patient is monitored while the effects of anesthesia wear off. Blood pressure, breathing, pain, nausea and the incision sites are assessed.
Hospital Stay: Some patients may go home on the same day or the following day, while others may need a longer stay depending on their health and recovery.
Pain Management: Temporary abdominal pain, bloating or shoulder-tip discomfort may occur because of the laparoscopy and the gas used during the procedure. Medicines are provided to manage pain and nausea.
Nutrition and Mobility: Fluids and food are restarted as tolerated. Patients are encouraged to walk as soon as it is safe.
Blood and Organ Monitoring: Blood counts, kidney function, liver function and electrolyte levels may be checked after treatment according to the chemotherapy used.
Incision Care: Instructions are provided for caring for the small incisions and recognising signs of infection.
Biopsy Review: Tissue samples are examined to assess the cancer and, after repeated procedures, may help evaluate whether the peritoneal disease is responding.
Further Treatment: Systemic chemotherapy or another treatment may continue between PIPAC procedures when recommended.
Repeated PIPAC: PIPAC is often planned as a series of procedures rather than a single treatment. Another cycle is considered only if the patient has recovered adequately and the team believes that further treatment remains appropriate.
Resuming Routine: Many patients resume light activities within several days, but recovery varies according to overall health, symptoms and other cancer treatments.
Follow-up Care: Follow-up appointments assess side effects, symptoms, blood results and response to treatment.

Key Advantages


- Fever, chills or increasing weakness
- Worsening abdominal pain that is not controlled by prescribed medication
- Increasing redness, warmth, swelling, discharge or bleeding from an incision
- Persistent vomiting or inability to eat or drink
- Increasing abdominal swelling or severe bloating
- Inability to pass urine, gas or stool as advised by the care team
- New or worsening diarrhoea, constipation or another unexpected change in bowel function
- Shortness of breath, chest pain or coughing up blood
- New swelling or pain in a leg
- Reduced urine output or a marked change in urine
- Unusual bruising, bleeding or persistent mouth ulcers
- Severe fatigue, dizziness, confusion or fainting
- Any symptom identified by the team as specific to the chemotherapy used

Continuum of Care
PIPAC is usually one part of a broader treatment pathway for peritoneal metastases. Patients may receive:



