




Stereotactic Radiosurgery (SRS) is a highly precise form of external beam radiation therapy used mainly to treat small, well-defined tumours and other abnormalities in the brain. Despite its name, it does not involve an incision or the surgical removal of tissue.
SRS directs multiple narrow radiation beams towards a precisely mapped target. Each beam delivers a limited dose as it passes through surrounding tissue, while the beams converge to deliver the prescribed treatment dose to the target.
Treatment may be delivered using different specialised platforms, including linear accelerator-based systems, Gamma Knife, CyberKnife or ZAP-X. SRS is traditionally delivered in one session. When treatment is divided over several sessions to protect nearby sensitive structures, it may be called fractionated stereotactic radiotherapy.
- One or more brain metastases
- Selected small primary brain tumours
- Meningiomas
- Vestibular schwannomas, also known as acoustic neuromas
- Pituitary adenomas
- Selected residual or recurrent gliomas
- Tumours at the skull base
- Residual tumours following surgery
- Recurrent tumours in previously treated areas where further radiation is considered safe
- Certain arteriovenous malformations
- Trigeminal neuralgia and selected other functional neurological conditions
- Patients who may not be suitable for open surgery because of the lesion’s location, their age or their overall health
- Patients who require treatment to a surgically inaccessible area
How Stereotactic Radiosurgery Is Performed
Before Treatment
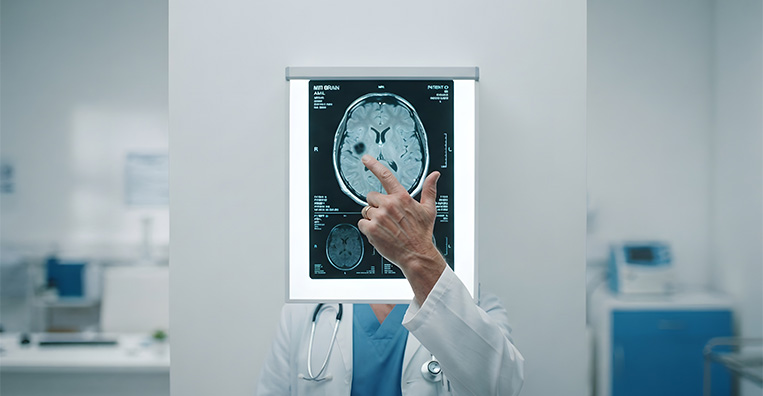
The radiation oncologist reviews the diagnosis, symptoms, imaging, previous treatments and medical history.
A neurosurgeon and other specialists may also be involved in evaluating and planning treatment.
A planning CT scan and high-resolution MRI are usually performed to define the target and surrounding structures.
Angiography or other specialised imaging may be required for certain vascular abnormalities.
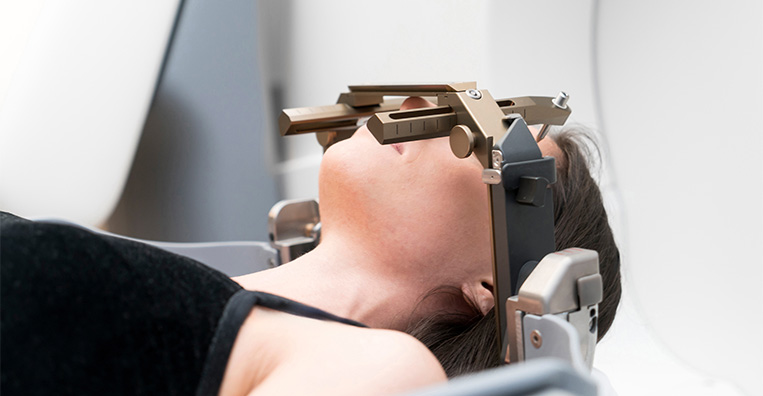
A customised thermoplastic mask may be prepared to help keep the head still during imaging and treatment.
For selected treatments, a rigid stereotactic head frame may be attached to the skull using small pins after local anesthesia.
The radiation oncologist, neurosurgeon where appropriate, medical physicist and treatment-planning team identify the target and calculate the radiation dose.
Multiple beam directions are planned to cover the target while limiting radiation exposure to nearby healthy brain tissue.
Medicines such as corticosteroids, anti-seizure medicines or anti-anxiety medication may be prescribed for selected patients.
Patients receive instructions about food, regular medicines and other preparation before treatment.

During Treatment
The patient lies on the treatment table with the mask or stereotactic head frame in place.
Imaging is used to verify the position of the target before radiation is delivered.
The treatment machine directs radiation beams towards the target from multiple planned angles.
The machine may rotate around the patient but does not touch them.
The patient must remain still but can communicate with the treatment team throughout the session.
The radiation cannot be seen or felt, and the treatment itself is painless.
Most adults remain awake and do not require general anesthesia.
Sedation or anesthesia may be considered for children or patients who cannot remain still.
A session may take approximately 30 minutes to several hours, depending on the platform, treatment plan and number of targets.
Treatment may be completed in one session or divided across several sessions when clinically appropriate.

After Treatment
A stereotactic mask is removed immediately after treatment.
If a head frame was used, it is removed and the pin sites are cleaned and covered if needed.
The patient may be observed for a short period before discharge.
Most patients can return home on the same day, although admission may be required based on their condition or symptoms.
Mild headache, tiredness, nausea or tenderness at the frame pin sites may occur.
Medicines such as corticosteroids may be prescribed or continued to manage swelling.
The patient is not radioactive and can safely be around other people.
Follow-up appointments are scheduled to monitor symptoms and treatment-related effects.
MRI, CT or other imaging is performed at planned intervals to assess the response.
The effect of SRS develops gradually, and the treated lesion may shrink or remain stable over several months.

Potential Benefits of Stereotactic Radiosurgery
- Non-invasive treatment without a surgical incision
- Precise delivery of radiation to a defined target
- Reduced radiation exposure to surrounding healthy brain tissue
- Protection of nearby critical structures through carefully planned beam delivery
- Treatment completed in one or a small number of sessions
- Outpatient treatment for most patients
- A shorter recovery period than open surgery for many patients
- Treatment of selected lesions that are difficult to reach surgically
- The ability to treat multiple brain metastases during the same treatment course, where appropriate
- An alternative for selected patients who cannot undergo surgery
- Additional treatment for certain residual or recurrent lesions
- Treatment of selected non-cancerous and vascular abnormalities

Side Effects of Stereotactic Radiosurgery
- Tiredness or fatigue
- Headache
- Nausea or vomiting
- Dizziness or temporary imbalance
- Mild scalp irritation or tenderness
- Temporary hair loss in the treated area
- Pain, swelling or minor bleeding at the head-frame pin sites, if a frame is used
- Swelling around the treated lesion, which may temporarily worsen existing symptoms
- Seizures in susceptible patients
- Delayed radiation changes in the treated brain tissue, including radiation necrosis
- Site-specific changes involving vision, hearing, balance, speech, memory, facial sensation or hormone function
- Rare injury to nearby nerves, blood vessels or healthy brain tissue
- A small long-term risk of developing another cancer related to radiation exposure



